
Vitamin D Deficiency, The Blood Test
Number Nobody Explains
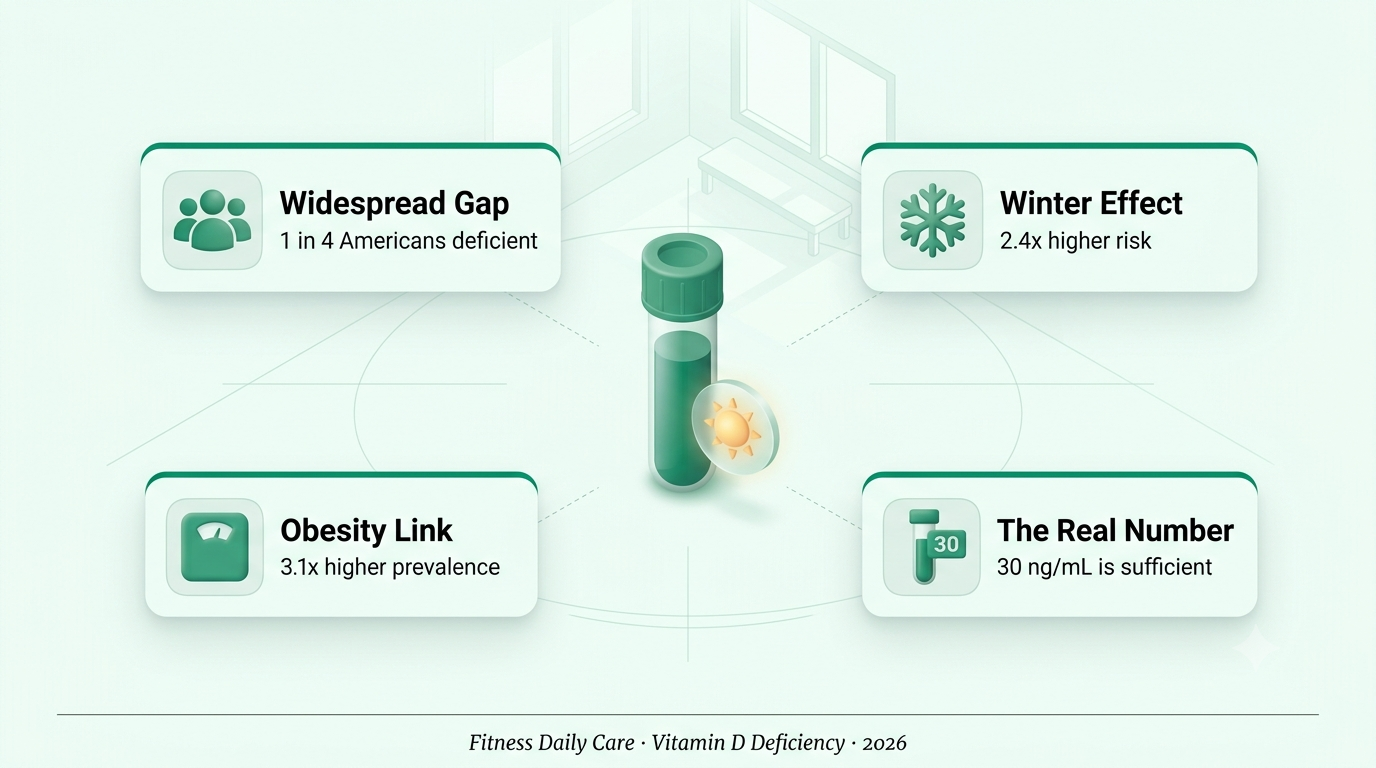
Roughly 1 in 4 Americans are vitamin D deficient, and most blood test results never explain what the number actually means
I never thought much about vitamin D deficiency until I saw my own blood test result — a number with “low” written next to it and no real explanation of what that meant. That sent me looking into what the number actually represents and why deficiency turns out to be this common in the first place.
Nearly a quarter of US adults are vitamin D deficient, and NHANES data puts the share below what’s considered a sufficient level closer to 41%. The gap between “deficient” and “sufficient” is both wider and more common than a single number on a lab report tends to make it feel.
This isn’t about mega-dosing on a hunch. It’s about what the blood test number actually means, who’s at the highest risk, and what dose the research actually supports for closing the gap.
Why It Matters Beyond Bones
Vitamin D supports calcium absorption and bone health, but it’s also involved in immune function — some research links low levels to elevated inflammation.
Sun Alone Often Isn’t Enough
Sunscreen use, northern latitudes, darker skin pigmentation, and winter months all significantly reduce synthesis, even with regular outdoor time.
Some Groups Are Hit Harder
Obese adults show roughly 3 times higher deficiency prevalence than non-obese adults; low milk intake and limited sun exposure add further risk.
The Number That Actually Matters
25-hydroxyvitamin D, or 25(OH)D, is the blood marker that measures status: under 20 ng/mL is deficient, 21–29 ng/mL is insufficient, 30+ is generally sufficient.
A number on a lab report doesn’t explain itself.
That’s exactly the problem.
What the Blood Test Number Means
Decode ItThe blood test that matters is 25-hydroxyvitamin D, written as 25(OH)D. A result under 20 ng/mL is considered deficient, 21 to 29 ng/mL is insufficient, and 30 ng/mL or above is generally considered sufficient. Some guidelines, including those focused on fall and fracture prevention in older adults, target the higher end of that range.
Who’s Actually at Risk
Risk FactorsDeficiency risk climbs sharply with several overlapping factors: obesity (roughly 3.1 times higher prevalence), winter months (about 2.4 times higher than summer), darker skin pigmentation, limited sun exposure, regular sunscreen use, and living at higher latitudes. These factors compound — someone with several of them at once faces meaningfully higher risk than any single factor suggests.
The Dose Research Supports
Dose GuideThe RDA is 600 IU/day for adults up to 70, and 800 IU/day after that, with a general safe upper limit of 4,000 IU/day without medical supervision. For confirmed deficiency, clinicians often prescribe higher, time-limited correction doses — commonly 50,000 IU once a week for 6 to 8 weeks, or 2,000 IU daily — followed by a lower maintenance dose.
Sun and Food Sources, What They Actually Cover
SourcesFatty fish, fortified milk, and egg yolks all contribute meaningful vitamin D, though few foods contain large amounts naturally. Sun exposure can generate vitamin D in skin, but the amount produced depends heavily on latitude, season, time of day, skin tone, and sunscreen use — which is exactly why so many people with regular outdoor time still test low.
More sun and more supplements
aren’t the same fix for every risk factor.
- Ask for a 25-hydroxyvitamin D test if you have risk factors — obesity, darker skin, limited sun exposure, or long winters where you live
- Know your number — under 20 ng/mL is deficient, 21–29 is insufficient, 30+ is generally sufficient
- Stick to 600–800 IU/day for general maintenance unless a clinician recommends otherwise
- Include food sources — fatty fish, fortified milk, and egg yolks all contribute
- Don’t self-prescribe correction doses — 50,000 IU/week protocols are meant to be supervised
⚠️ Where the Evidence Has Limits
1. More isn’t automatically better. The general safe upper limit is 4,000 IU/day; higher correction doses are meant to be short-term and medically supervised, not a standing daily habit.
2. Toxicity is rare but real. Most reported cases come from dosing errors rather than typical supplementation, with symptoms like nausea, weakness, and kidney issues at extreme levels.
3. Not everyone needs routine testing. Testing is most useful for people with known risk factors or symptoms, rather than as a blanket recommendation for the general population.