
Iron Deficiency in Women, The Fatigue
Nobody Tests For
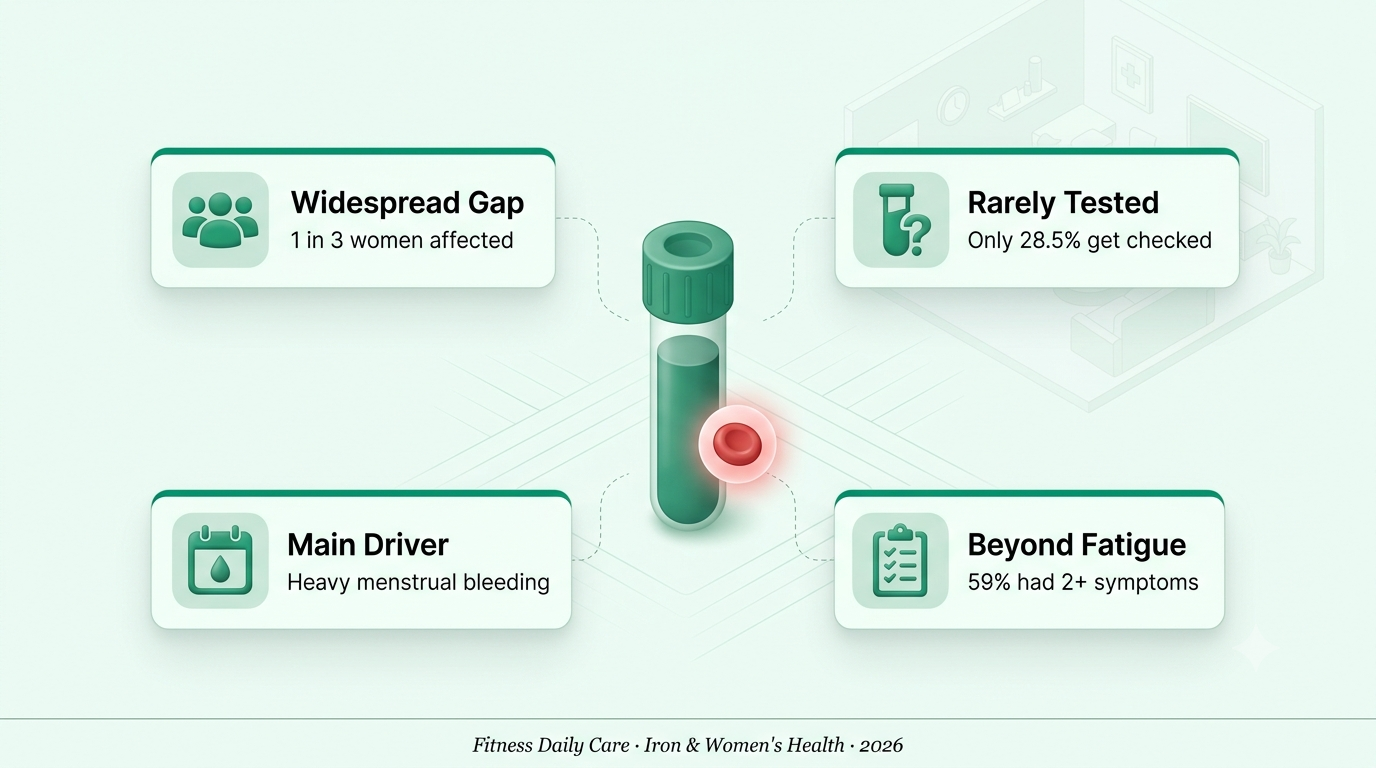
Nearly 1 in 3 US women have iron deficiency, and standard bloodwork often misses it entirely — here’s the test and symptoms most people never hear about
I kept seeing the same pattern come up in the iron deficiency in women research: patients reporting fatigue, getting told their labs are “normal,” and never actually receiving the one test that would have caught it. That test is ferritin, and it’s ordered far less often than you’d expect.
Iron deficiency is the most common nutrient deficiency among US women, affecting close to a third of them. But standard bloodwork often stops at hemoglobin, which only flags the problem once it’s progressed all the way to anemia. Ferritin, the marker that catches iron deficiency earlier, gets checked in only a minority of patients — even among those already reporting fatigue.
This isn’t about self-diagnosing. It’s about knowing which symptoms are worth mentioning, which test to ask for by name, and why “normal” hemoglobin doesn’t necessarily mean iron stores are fine.
Why It Causes Fatigue
Iron is essential for hemoglobin’s oxygen transport and for enzymes involved in cellular energy production — low stores reduce both, even before anemia sets in.
Standard Bloodwork Misses It
Routine panels often check hemoglobin only, which can stay in the normal range until iron stores are already significantly depleted.
Menstrual Blood Loss
Heavy menstrual bleeding is the leading cause among reproductive-age women — one study of 394 teens found 40% had iron deficiency alongside heavy bleeding.
It’s More Than Fatigue
Clinical studies of iron-deficient women found hair loss, restless legs, cracked mouth corners, and unusual cravings, often occurring together.
Normal hemoglobin doesn’t mean normal iron.
It just means the deficiency hasn’t caught up yet.
The Symptoms Beyond Fatigue
Often MissedA clinical study of iron-deficient women of reproductive age found a cluster of non-hematological symptoms: diffuse hair loss in 55.9%, cracked mouth corners (cheilitis) in 20.6%, restless legs syndrome in 20.6%, and unusual cravings for non-food items (pica) in 32.4%. Nearly 59% of the women studied had two or more of these symptoms together.
Why It’s Often Missed
Testing GapIron deficiency progresses in stages: iron stores drop first, and hemoglobin only falls later, once stores are significantly depleted. A large primary care cohort found that only about 28.5% of patients ever received a ferritin test — the marker that catches deficiency at the earlier, nonanemic stage. Fatigue did roughly double the odds of getting tested, but most patients still weren’t.
The Main Driver: Menstrual Blood Loss
Root CauseHeavy menstrual bleeding is the leading cause of iron deficiency in reproductive-age women. In a study of 394 adolescent girls, 53% reported heavy menstrual bleeding, and 40% had confirmed iron deficiency — the two conditions clustering together clearly enough that clinicians researching this now recommend asking about bleeding patterns whenever iron deficiency comes up.
What Actually Fixes It
TreatmentIn a clinical trial, women with iron deficiency anemia who took oral iron (ferrous sulfate) for 8 weeks showed measurable improvement in iron status, cognitive function, and the non-hematological symptoms described above. The takeaway isn’t “supplement blindly” — it’s that confirmed deficiency, once identified, responds well to targeted treatment.
The fatigue was real.
It just took the right test to prove it.
- Ask for ferritin specifically — not just a CBC or hemoglobin check, which can miss nonanemic deficiency
- Track menstrual bleeding patterns — unusually heavy or prolonged periods are the most common driver
- Note non-fatigue symptoms — hair loss, restless legs, unusual cravings, and cracked mouth corners are worth mentioning
- Pair iron-rich foods with vitamin C — this combination meaningfully improves absorption
- Don’t start high-dose supplements without testing first — confirm deficiency before treating it
⚠️ Where the Evidence Has Limits
1. Don’t self-supplement blindly. Iron overload is possible and can be harmful, especially for anyone with hemochromatosis or a similar condition — a ferritin test should guide whether supplementation makes sense.
2. Oral iron can cause GI side effects. Constipation and nausea are common; dosing, formulation, and timing relative to food all affect tolerability, and a clinician can help fine-tune the regimen.
3. Fatigue has many causes. Iron deficiency is common enough to be worth testing for, but it’s one of several possible explanations, not an automatic diagnosis.