
Swollen Calves Aren’t Always Age,
It’s What You Do for 8 Hours a Day
8 hours of sitting raises calf volume 2.4%. The real drivers behind swollen calves are sedentary work, sodium, and a weak calf pump — not aging.
Most people blame swollen calves on getting older. The evidence points somewhere else entirely. When your calves feel puffy by 5 p.m., the reflex is to write it off as age, weather, or “just how it is.” That reflex is wrong for the majority of otherwise healthy adults under 60. What actually drives most cases of swollen calves is a specific mechanical failure — the calf muscle pump, sometimes called the “second heart,” stops moving venous blood back up toward the chest, and fluid pools in the lower legs.
The Centers for Disease Control and Prevention estimates that chronic venous disease affects roughly one in four US adults, and the rate climbs sharply with sedentary hours. Americans spend about 55% of their waking day sitting — around 7.7 hours. In lab conditions, 8 hours of uninterrupted sitting increases calf circumference by 2.4% and traps roughly 10% more extracellular water in the lower-leg muscles. That is not aging. That is a workday.
The remote work shift made this measurably worse. Home-based workers sit longer than office workers, take fewer natural movement breaks, and lose the incidental activity that a physical office builds in — walking to conference rooms, moving between floors, going out to lunch. Vascular specialists are seeing earlier presentations of venous symptoms in people in their late 20s and 30s, and desk-based careers are the common thread. This is not coincidental. It is a direct consequence of the workday shape changing while human circulation biology stayed the same.
This piece breaks down the four lifestyle drivers behind swollen calves that actually matter, the red-flag pattern that means you need a doctor within 24 hours, and a concrete daily template — including the break interval most vein specialists agree on. The framework draws from Mayo Clinic and Cleveland Clinic clinical guidance, CDC and FDA population data, the American Heart Association’s position on sedentary vascular risk, and a peer-reviewed 8-hour sitting trial published in Medicine & Science in Sports & Exercise. What follows is what the evidence actually says once the “you’re just getting older” framing gets removed.
The problem is mechanical, not medical
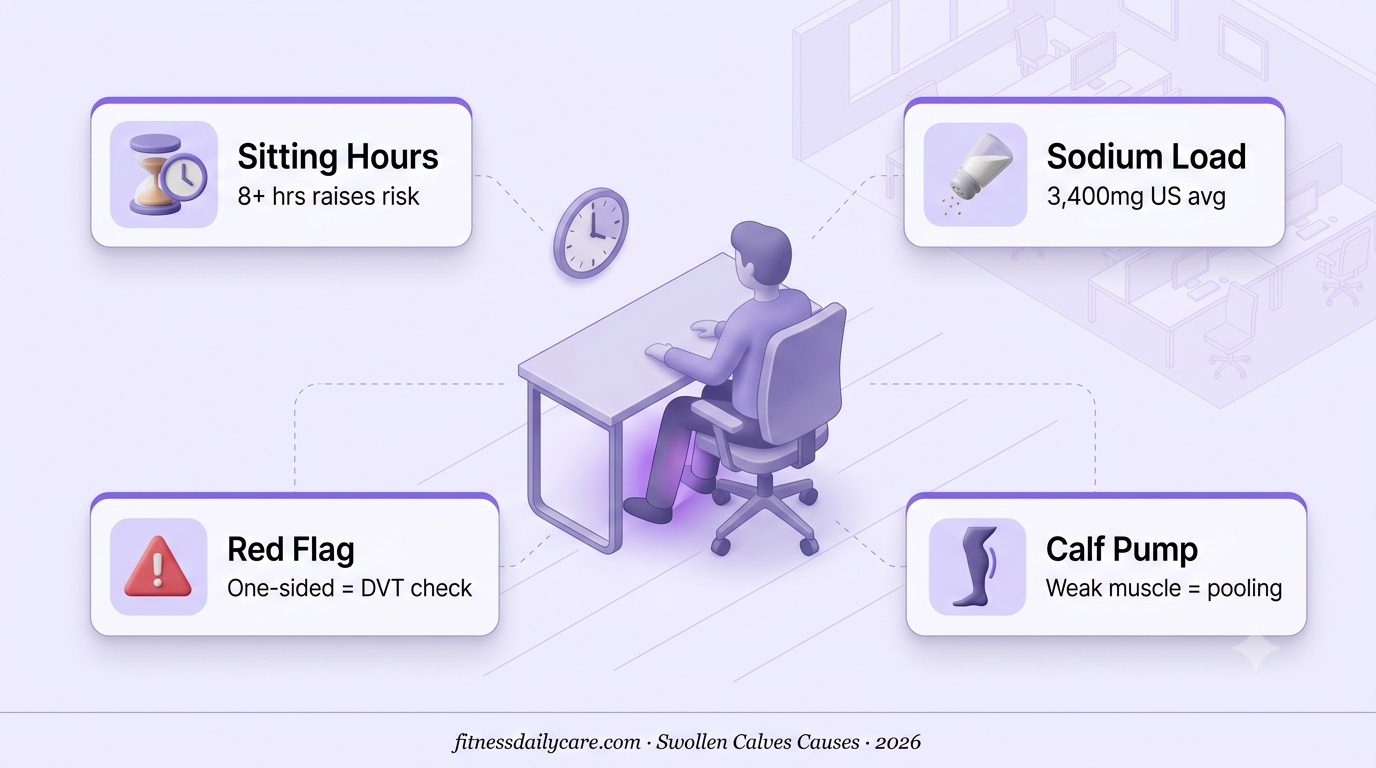
Your calf muscles are the primary pump returning venous blood from the legs. When they don’t fire for hours, blood pools and fluid seeps into tissue. Not disease, not aging — physics.
Sodium isn’t the villain most people think
Salt matters — 3,400mg vs the 2,300mg limit adds fluid retention. But even a low-sodium day of pure sitting still swells your calves. Movement outranks diet here.
Two minutes of walking beats standing all day
Standing desks alone don’t fix this — vein specialists have seen more venous issues from people who stand still. What works is contraction: walking, calf raises, ankle pumps.
One-sided swelling is the red flag
Both calves puffy after work? Almost always lifestyle. One calf suddenly larger, warm, tender, or discolored? That’s a same-day medical call — possible DVT.
Your heart pumps blood down.
Your calves pump it back up.
When they stop, everything pools.
The 4 Lifestyle Drivers Behind Swollen Calves
Sitting 8+ Hours (The Biggest Lever)
#1 CauseThe most controlled evidence on swollen calves comes from an 8-hour sitting trial published in Medicine & Science in Sports & Exercise. Healthy adults sat continuously for a workday. Result: calf circumference rose 2.4%, ankle circumference rose 2.7%, extracellular water in the lower-leg muscles increased 10.1%, and arterial blood flow dropped to roughly 61% of baseline. Every measurable circulation marker got worse. In a separate middle-aged cohort, just 2 hours of continuous sitting was enough to produce noticeable tension, heaviness, and swelling symptoms.
This is not about being unhealthy. This is what happens to the average human leg when the calf muscles stop firing. The Cleveland Clinic and the American Heart Association both flag prolonged sitting as a specific risk factor for venous pooling and, at the extreme, deep vein thrombosis. The post-2020 shift to remote and hybrid work made this worse — home-based workers sit longer, break less often, and lose the incidental walking that a normal office builds in (walking to meetings, moving between floors, going to lunch). One separate research group at the same lab found that even 4 hours of continuous sitting produced enough lower-leg edema to raise inflammatory markers, and that a brief 3-minute exercise bout every hour was enough to reverse most of that inflammation. The dose-response is that clean.
The mechanism, briefly: your heart pumps blood down to the legs with force, but returning that blood upward against gravity requires a second pump — the calf muscles squeezing the deep veins with each contraction. When you sit, the calves are relaxed, one-way venous valves alone can’t handle the hydrostatic pressure, and blood pools in the lower legs. Fluid then filters out of the veins into surrounding tissue. That is the swelling. Standing helps a little because the anti-gravity postural muscles fire, but only for a few minutes before they fatigue. Actual contraction — walking, calf raises, foot pumps — is what restarts the system.
Sodium Above 3,400mg (Fluid Retention You Can Measure)
#2 CauseThe FDA reports that the average American adult consumes about 3,400mg of sodium per day — nearly 50% above the 2,300mg upper limit set by the Dietary Guidelines for Americans. The CDC estimates that around 90% of US adults regularly exceed the 2,300mg cap. About 40% of that sodium comes from six categories: breads, pizza, sandwiches, cold cuts, soups, and savory snacks. Restaurant meals routinely deliver a full day’s sodium in a single sitting.
Here is the mechanism most people miss: sodium doesn’t just raise blood pressure over years. It also drives immediate, measurable fluid retention. Extra sodium pulls water into the extracellular compartment. Blood volume rises, capillary pressure in the lower legs rises, and more fluid filters out into the tissue — which shows up as swollen calves and puffy ankles by evening, especially after a takeout dinner. Cleveland Heart notes that this bloating typically resolves within 24 to 48 hours of returning to a lower-sodium intake. So the swelling is real, and reversible, but repeats every time the intake spikes.
The tricky part is that most sodium is invisible. Only a small percentage comes from the salt shaker at the table. The bulk comes from processed and restaurant foods where the sodium is already baked into the recipe — a Panera sandwich clears 1,500mg, a Chipotle bowl with chips and salsa clears 2,500mg, a single frozen dinner can carry 900 to 1,400mg. Two of those in one day and you are over the limit before dinner. This is why swollen calves often correlate with days you ate out or ordered in, and why home-cooked weeks tend to show visibly slimmer ankles by Friday.
Weak Calf Pump (Your “Second Heart” Isn’t Trained)
#3 CauseThe calf muscles — mostly the soleus and gastrocnemius — function as the primary pump returning venous blood from the legs back to the heart against gravity. The Cleveland Clinic and the American Heart Association both refer to this as the “second heart.” Research published in the Journal of Biomechanics found that people with smaller or weaker calf muscles show poorer circulation efficiency and heavier reliance on the heart itself. When the pump underperforms, venous blood stagnates. Over time this produces the clinical picture of chronic venous insufficiency: leg heaviness, swelling, skin changes, and, at its most visible, varicose veins.
Two things weaken this pump. First, chronic under-use — years of sitting without loaded calf work. Second, restricted ankle mobility. If the ankle can’t fully dorsiflex and plantarflex, the calf can’t contract through its full range, and each “pump stroke” moves less blood. The result is that even when you do walk, the pump is inefficient. This is why office workers who take up walking often notice their calf swelling improves quickly but not completely — the muscle is still under-trained.
There is also a subtler failure mode that shows up in people who exercise regularly but always in the same pattern. Cyclists, for example, get plenty of leg work but the calf contraction pattern is limited by the pedal stroke. Runners with a heavy heel strike underuse the soleus. Weightlifters who skip direct calf work altogether have strong quads and glutes but a weak second heart. Direct calf training — standing calf raises, seated calf raises for the soleus, walking on toes for a minute at a time — closes this gap in a few weeks. It is the least glamorous piece of fitness programming and one of the highest returns on effort for anyone with a desk job.
Dehydration & Alcohol (The Counterintuitive One)
#4 CauseThis one is counterintuitive because most people assume swollen calves means “too much water” and cut fluids. That backfires. When you are underhydrated, your body actively retains sodium and water to protect blood volume — which increases the fluid retention that drives swelling. The Mayo Clinic and vascular specialists routinely tell patients with mild dependent edema to drink more, not less. Aim for pale yellow urine as the practical benchmark.
Alcohol makes this worse in two ways. First, alcohol is a diuretic that dehydrates you within hours, triggering the same sodium-retention response the next morning. Second, most drinks people order with food are high-sodium contexts — cocktails with salted rims, beer with pretzels, wine with charcuterie. A Saturday night out often produces very visible swollen calves by Sunday afternoon that most people incorrectly attribute to “just being tired.” The compounding effect of alcohol, sodium, and next-day sitting is the largest single-day swelling driver most desk workers experience.
Air travel deserves its own note in this section because it stacks every driver at once — you are sitting for hours in a low-humidity environment that dehydrates you faster than usual, cabin pressure changes affect venous return, and airline food is high sodium. A single long-haul flight can produce measurable calf swelling that lingers for a day or two. The CDC and Mayo Clinic both recommend walking the aisle every hour, doing seated ankle pumps continuously, wearing knee-high compression socks (15 to 20 mmHg), and drinking water aggressively throughout the flight. This is also the highest-risk situation for DVT in otherwise healthy adults — the term “economy class syndrome” refers specifically to this combination.
⚠️ When Swollen Calves Are a Medical Emergency
1. One-sided swelling that appears suddenly. Bilateral, symmetric swelling by end of day is almost always lifestyle. Unilateral swelling — one calf visibly larger than the other, appearing over hours — is the classic DVT presentation. Compare left and right side by side. If there is a clear size difference, call your physician the same day.
2. Pain that doesn’t respond to stretching or elevation. A muscle cramp resolves with rest, ice, or a stretch. DVT pain persists or worsens with movement and does not improve with massage. It typically feels like a deep, throbbing ache in the back of the calf, distinct from a pulled muscle.
3. Warmth, redness, or skin discoloration in one leg. Skin over a DVT feels notably warmer than the other leg to the touch. It may appear reddish, bluish, or purplish. Combined with swelling, this is a same-day medical evaluation.
4. Shortness of breath or chest pain — call 911. A DVT that breaks loose becomes a pulmonary embolism, which is life-threatening. Sudden shortness of breath, chest pain that worsens with breathing, rapid heartbeat, coughing up blood, or fainting after leg swelling episodes are emergency-room signs. Do not drive yourself.
A Realistic Anti-Swelling Day for Desk Workers
The framework below is what most vascular specialists actually recommend for the working adult with mild, bilateral, end-of-day swollen calves who is not showing red flags. It is intentionally modest — every item is something you can install into a normal workday without changing your job, your gym schedule, or your grocery budget. The goal is not to eliminate all lower-leg fluid movement (that is neither possible nor healthy) but to keep the calf pump firing often enough that the pooling never accumulates into visible swelling. Consistency beats intensity here. A person who takes seven 2-minute walking breaks and drinks water on schedule will see faster and larger improvement than someone who does one hard 45-minute gym session and then sits motionless for the rest of the day. Think of the day as a series of small pump activations rather than one big fix — the biology follows that pattern too.
- Every 30 minutes. Stand up, walk to the water station or restroom, sit back down. 2 minutes is the minimum. Set a repeating timer for the entire workday.
- Seated ankle pumps. While working, flex your feet up and down 10 to 20 times every 30 minutes. This activates the calf pump without leaving your chair.
- Sodium check. Aim under 2,300mg per day. Scan labels on bread, deli meat, canned soup, and frozen meals — those are the quiet contributors, not the salt shaker.
- Hydration target. Roughly half your body weight in ounces of water per day. Pale yellow urine is the benchmark. Under-hydration causes swelling; over-hydration doesn’t fix it.
- End-of-day elevation. Lie down with your heels propped 5 to 6 inches above heart level for 10 to 15 minutes. This drains pooled fluid and drops evening calf circumference measurably.
- Compression socks (optional, evidence-backed). Low-pressure knee-high compression socks (15 to 20 mmHg) worn during long sits or flights cut calf swelling significantly per clinical trials. Not medical unless prescribed higher.
- Twice-weekly calf training. 3 sets of 15 to 20 bodyweight calf raises, 2 to 3 times per week. This trains the pump for the long game.
Standing desks alone don’t fix this.
Contraction is what moves blood.
You have to actually pump.